
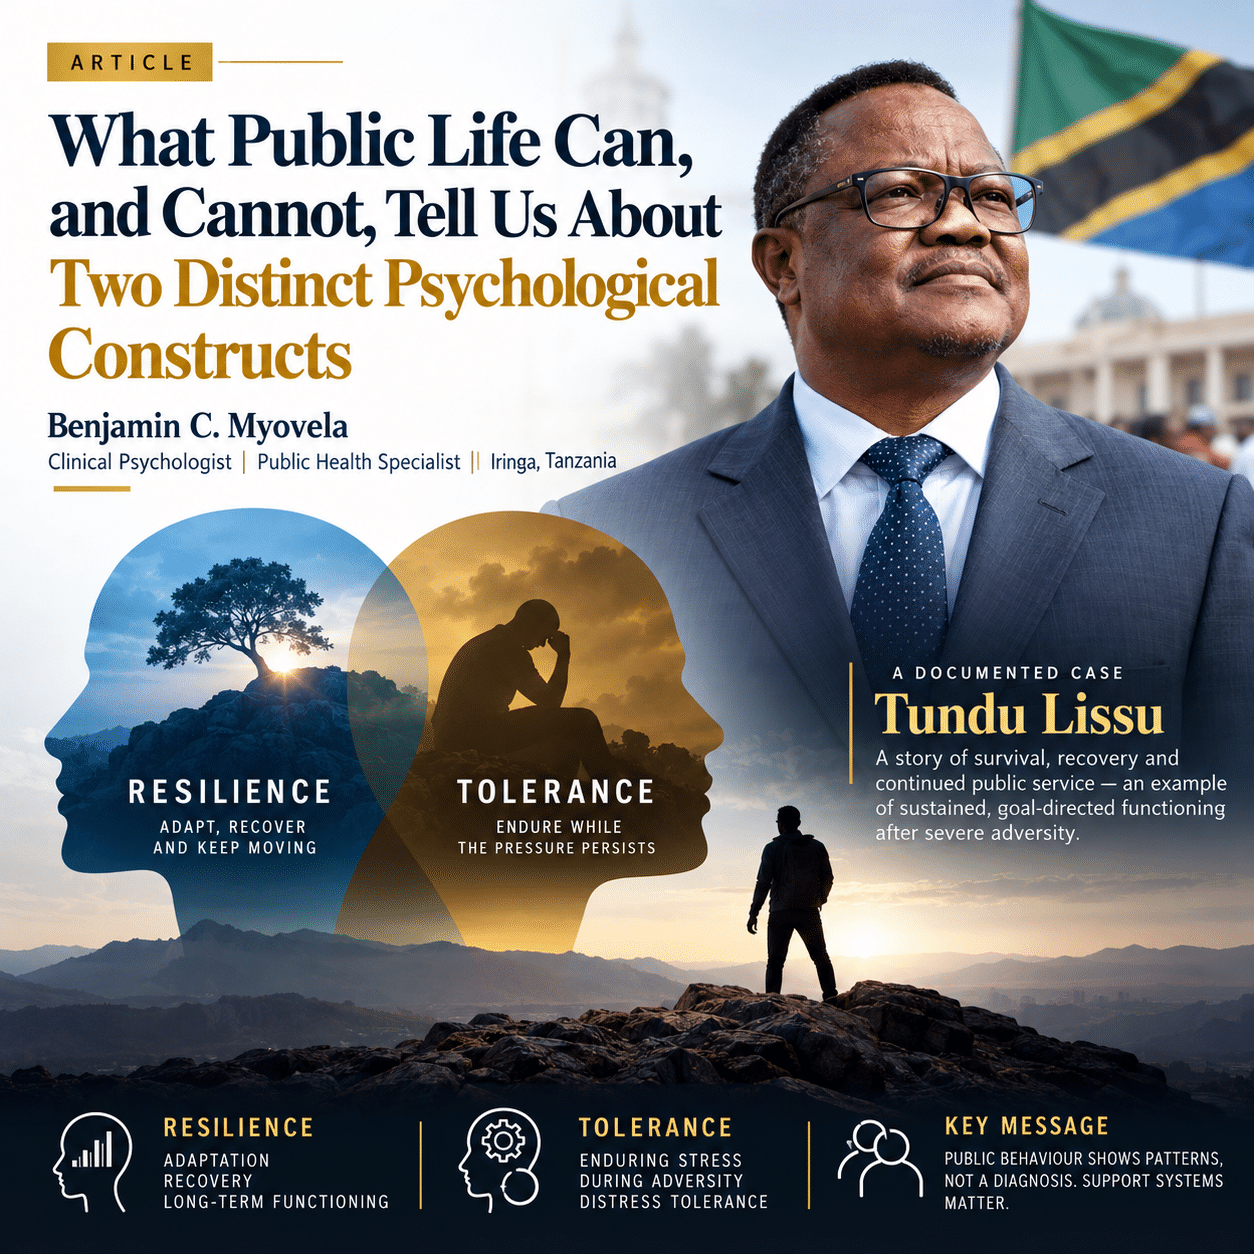
What Public Life Can, and Cannot, Tell Us About Two Distinct Psychological Constructs
Benjamin C. Myovela
Clinical Psychologist | Public Health Specialist | Iringa, Tanzania
Abstract. Resilience and tolerance are often used interchangeably, yet they describe different psychological processes that operate on different timelines. This article distinguishes the two constructs and examines the publicly documented history of Tundu Lissu as an illustrative case of sustained, goal-directed functioning after severe adversity. It also sets out the limits of inference from public behaviour, and considers what the distinction means for leaders, organisations and mental health professionals.
Introduction
In everyday conversation, resilience and tolerance are frequently treated as synonyms for “toughness.” In psychology they are related but distinct constructs. They describe different processes, operate on different timelines, and call for different kinds of support. Clarifying the distinction is not merely academic: it shapes how clinicians assess people, how organisations design wellbeing programmes, and how the public interprets those who endure hardship in full view.
Defining the Constructs
Resilience is the capacity to adapt to, recover from, or continue functioning through adversity or trauma. It is best understood as a dynamic process rather than a fixed trait, shaped by cognitive, emotional, behavioural, interpersonal and environmental resources (Masten, 2001). In the trauma literature, resilience is often described as a trajectory: the ability to maintain or regain stable functioning after significant stress (Bonanno, 2004).
Tolerance is the capacity to endure ongoing stress, frustration or discomfort without a disproportionate reaction. It overlaps with the constructs of distress tolerance and frustration tolerance (Simons & Gaher, 2005). Where resilience concerns adaptation and recovery over time, tolerance concerns how a person holds up while the adversity is still unfolding.
The two are not interchangeable. A person may show high tolerance during an ongoing crisis yet struggle with long-term recovery. Another may recover well after an event but tolerate continuing stress poorly. Understanding either requires attention to context, timeline and domain.
| Dimension | Resilience | Tolerance |
| Core question | How does a person adapt and recover? | How does a person hold up while stress persists? |
| Timeframe | Process unfolding over time, often after the event | Capacity operating during the adversity |
| Related concepts | Adaptation, recovery, growth, trajectories of functioning | Distress tolerance, frustration tolerance |
| Key influences | Cognitive, emotional, behavioural, interpersonal and environmental resources | Regulation skills, appraisal of threat, available supports |
Table 1. Resilience and tolerance compared.
A Documented Case
The publicly documented life of Tundu Lissu offers an instructive case in both constructs. On 7 September 2017, Lissu was shot 16 times outside his parliamentary residence in Dodoma. Public reporting documents more than 20 surgeries by 2018, with further procedures later. After years abroad in treatment and rehabilitation, he returned to Tanzania in July 2020 and re-entered the presidential race. He has since described others’ surprise at his resilience, and has spoken of the experience reshaping his outlook and leaving him seeing himself as a survivor.
From a psychological standpoint, what stands out is not survival alone but the pattern that followed: prolonged medical recovery, return from exile, resumption of high-demand political activity, and continued public engagement despite ongoing legal and political pressures documented by bodies such as the Inter-Parliamentary Union.
Resilience. Sustained, goal-directed re-engagement after severe adversity maps closely onto how resilience is defined in the literature: functioning was not merely preserved but rebuilt and redirected toward valued goals.
Tolerance. Continuing to function publicly under chronic threat, uncertainty, legal pressure and hostility requires a considerable capacity to hold distress without being overwhelmed by it. This does not imply that distress is absent; it suggests that distress is carried alongside purposeful action. In clinical terms, this is consistent with a high threshold for distress tolerance under conditions of chronic external threat.
The Limits of Inference
None of this constitutes a clinical assessment. Public behaviour is only a partial window into psychological functioning, and both resilience and tolerance vary by domain and across time. Assigning a clinical grade or diagnosis from the public record alone is methodologically unsound and, in professional ethics, inappropriate; the principle underlying the so-called Goldwater Rule reflects this (American Psychiatric Association, 2013). Valid conclusions require validated instruments and direct assessment.
What can fairly be said is narrower, and still meaningful: the documented history shows sustained perseverance and adaptive re-engagement under extreme adversity. It is worth examining as a case study, without overstating what public observation can prove.
Implications for Practice and Leadership
For leaders, organisations and mental health professionals, the distinction carries practical weight. Resilience is not simply individual grit. It is supported or undermined by safety, access to healthcare, social connection, a sense of purpose, and institutional conditions. Tolerance, meanwhile, has limits, and enduring harm should never be romanticised as a virtue.
The more useful question is therefore not only “How did this person endure?” but also “What made endurance necessary, and what support made recovery possible?” Framed this way, the conversation shifts from admiring individual strength to examining the conditions that enable, or fail to enable, recovery.
Conclusion
Public life can reveal patterns; it cannot deliver a diagnosis. But it can remind us that resilience is not the absence of struggle. It is the capacity to keep moving through struggle, often with help.
Keywords: resilience; distress tolerance; trauma recovery; psychological adaptation; leadership; public health; Tanzania
Selected References
American Psychiatric Association. (2013). Principle 7.3 of the Principles of Medical Ethics with annotations especially applicable to psychiatry (the “Goldwater Rule”).
Bonanno, G. A. (2004). Loss, trauma, and human resilience: Have we underestimated the human capacity to thrive after extremely aversive events? American Psychologist, 59(1), 20–28.
Masten, A. S. (2001). Ordinary magic: Resilience processes in development. American Psychologist, 56(3), 227–238.
Simons, J. S., & Gaher, R. M. (2005). The Distress Tolerance Scale: Development and validation of a self-report measure. Motivation and Emotion, 29(2), 83–102.


